Personalized Plastic Surgery & Aesthetic Care in Seocho-gu, Seoul

Medical Guide
What Gynecomastia Correction Involves, Step by Step
Gynecomastia correction is a sequence of steps: medical workup, tissue assessment, surgery, compression, and follow-up. Here is what each stage involves.
Schedule a ConsultationWhat Is Involved in Gynecomastia Correction, From Workup to Follow-Up
Medically reviewed by Dr. In-Ho Khang, MD, Yonsei University College of Medicine; Chief Academic Director of Plastic Surgery, Korean Society of Aesthetic Surgery & Laser (KSASL)
Gynecomastia correction is not a single event on an operating table. It is a sequence: finding out why the tissue is there, examining the chest to establish what it is made of, agreeing on what the operation will remove, preparing your body and your medication list, the surgery, then weeks of compression, wound care, and scheduled review. This article walks through that sequence in order.
Step One: Finding Out Why the Tissue Is There
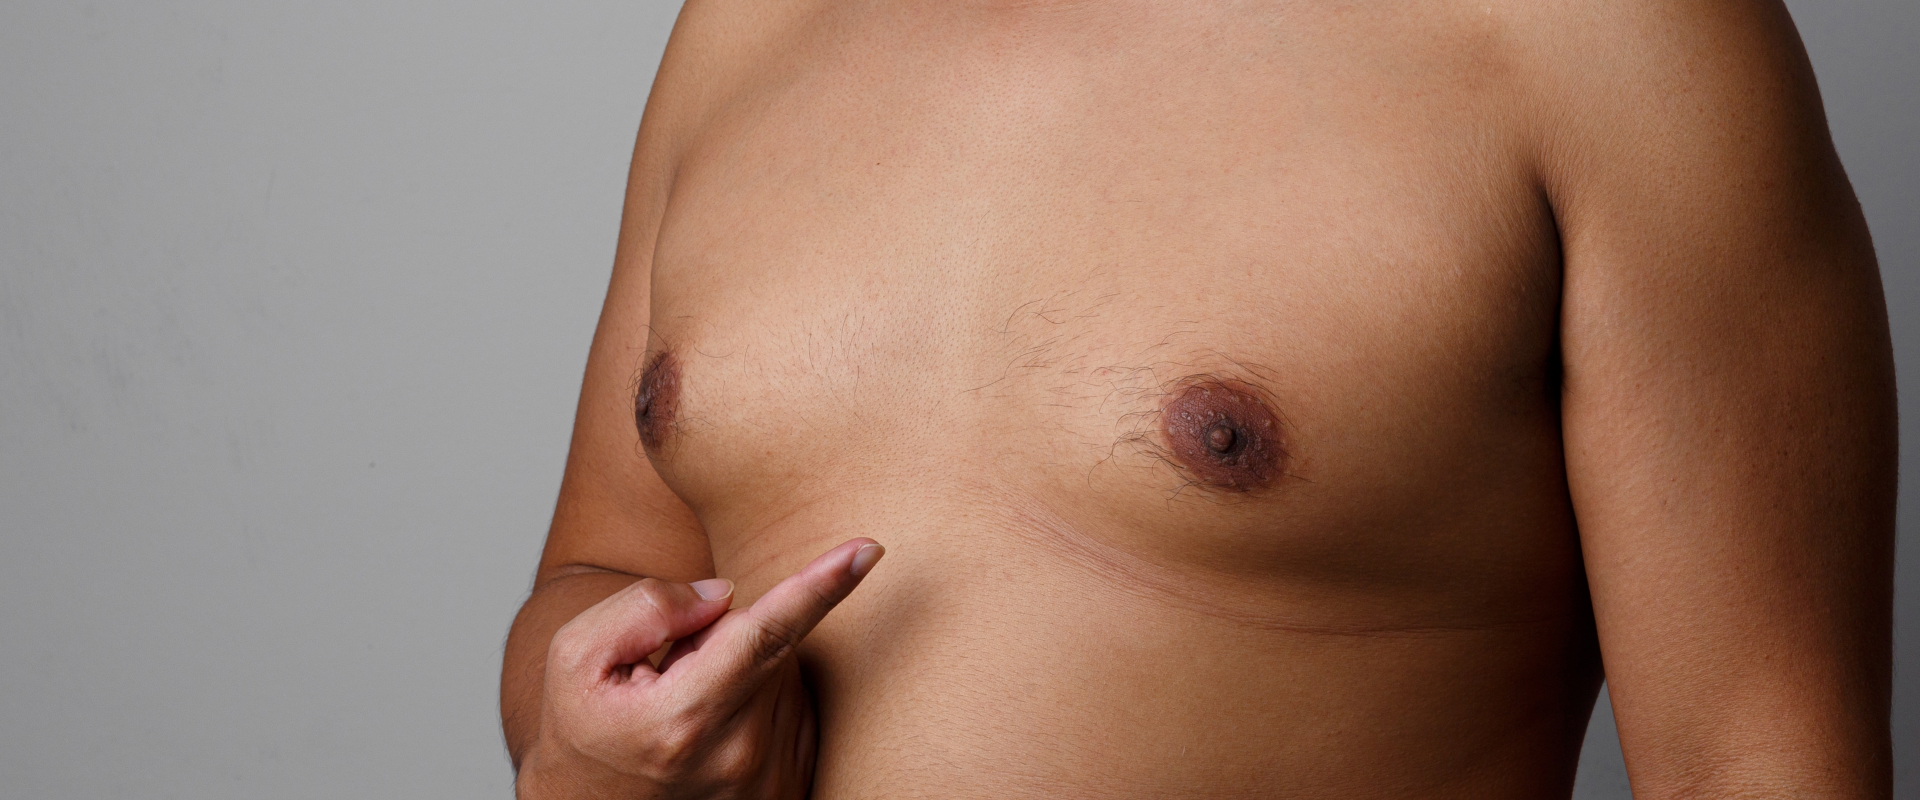
Enlarged male breast tissue is a finding, not a diagnosis. MedlinePlus describes gynecomastia as an abnormal amount of breast tissue developing in males, usually driven by an imbalance between estrogen and testosterone, and notes that the first task is to establish whether the growth is breast tissue at all rather than excess fat.
The cause matters too. MedlinePlus lists chronic liver disease, kidney failure and dialysis, low testosterone, and obesity among the health conditions that can produce breast growth in adult men, with thyroid disorders and pituitary tumors among the rarer causes. It also lists a long roster of medications, including treatments for prostate enlargement and prostate cancer, finasteride for hair loss, HIV medicines, corticosteroids and anabolic steroids, some heartburn and heart medicines, certain antifungals and antibiotics, and opioids. It advises not stopping any medicine without speaking to a provider first, because changing a causative drug is sometimes the treatment.
What a workup usually looks like
Mayo Clinic describes the assessment as starting with questions about symptoms and medications, followed by an examination of the breast tissue, abdomen, and genitals. It lists blood tests, mammograms, CT scans, MRI scans, testicular ultrasound, and tissue biopsy among the tests that may be ordered, either to identify a cause or to check for look-alike conditions. MedlinePlus notes that enlarged breasts are a recognized symptom of low testosterone in males who have completed puberty.
Mayo Clinic also lists the conditions mistaken for gynecomastia: fatty breast tissue, sometimes called pseudogynecomastia, which needs no further testing once identified; breast cancer, uncommon in men but possible; mastitis; and lipoma, a benign fatty lump.
The findings that change the conversation
MedlinePlus advises contacting a provider for recent swelling, pain, or enlargement in one or both breasts, dark or bloody nipple discharge, a skin sore or ulcer over the breast, or a lump that feels hard or firm. Mayo Clinic states the concern directly: enlargement of one breast, or a firm lump, raises the possibility of male breast cancer. If any of those apply, the next appointment is a medical one.
Step Two: The Consultation and the Physical Assessment
The consultation is where the operation is designed, and it is more clinical than most people expect. The American Society of Plastic Surgeons states that you should be prepared to discuss your surgical goals, medical conditions and drug allergies, current medications, vitamins, herbal supplements, alcohol, tobacco and recreational drug use including steroids, and previous surgeries.
ASPS also sets out what the surgeon does. The list includes evaluating your general health and pre-existing risk factors, performing diagnostic testing to determine the underlying cause — which may include testing of endocrine function — examining the breasts and taking measurements of size, shape, skin quality, and nipple and areola position, taking photographs for your records, discussing options and outcomes and risks, and discussing the use of anesthesia.
YONSEI LEEDS CLINIC describes the same shape of visit. The clinic states that patients receive an individual consultation with Dr. In-Ho Khang covering chest tissue composition, severity, and treatment goals, and that international patients can complete a pre-arrival teleconsultation covering their presentation, concerns, and medical history before traveling to Korea.
Step Three: Deciding What the Operation Will Actually Remove
Everything downstream — incision placement, recovery length, scar pattern — follows from one question answered by hand at the examination: is this chest glandular, fatty, or both?
Mayo Clinic frames the two surgical options plainly. Liposuction removes breast fat but not the breast gland tissue itself. Mastectomy removes the gland tissue, and with smaller amounts of gland it can be done through small incisions, which shortens recovery. Mayo Clinic adds that the two are sometimes combined.
The clinic's published position matches that logic. It states that gynecomastia may involve firm glandular tissue beneath the nipple, excess chest fat, or both, and that accurate assessment of tissue composition is important when selecting the approach. It states that glandular tissue does not respond to lifestyle change the way excess fat does, so exercise or weight management alone may not reliably correct true glandular gynecomastia. It states that treatment may accordingly involve glandular excision, liposuction-based fat reduction, or a combination, and that Dr. Khang distinguishes glandular, fatty, and mixed presentations before choosing.
Leave the consultation knowing which of those three plans is proposed for you, where the incisions will sit, and what is expected to remain palpable under the areola once healing is finished.
Questions Worth Asking Before You Consent
ASPS publishes a consultation checklist worth using verbatim. Its credential questions cover board certification, whether the surgeon trained specifically in plastic surgery, how many years of that training they have had, whether they hold hospital privileges for the procedure, and whether the surgical facility is accredited or state-licensed.
The clinical half is just as useful: am I a good candidate, what will be expected of me, where and how will the procedure be performed, what technique is recommended for me, how long a recovery should I expect, what are the risks, how are complications handled, what are my options if I am dissatisfied, and are there before-and-after photographs.
Two questions need translating for a surgeon practicing outside the United States. American Board of Plastic Surgery certification is a US credential and does not apply to a Korean surgeon; the Korean equivalent is a national specialist qualification that a US reader cannot look up in any public individual registry, so the practical substitute is asking to see the certificate itself. Likewise, "how are complications handled" carries more weight when you will be on another continent within weeks.
Step Four: Preparing in the Weeks Before Surgery
ASPS states that in preparing for gynecomastia surgery you may be asked to get lab testing or a medical evaluation, to take certain medications or adjust your current ones, to stop smoking, and to avoid aspirin, anti-inflammatory drugs, and herbal supplements because they can increase bleeding. It adds that you should arrange for someone to take you home and stay with you for at least the first night.
Cleveland Clinic's anesthesia preparation guidance adds specifics. It advises giving your care team a current list of all medications, vitamins, and supplements, avoiding food and drink for eight hours before you arrive unless told otherwise, stopping herbal supplements one to two weeks beforehand as directed, and taking certain blood pressure medicines with a sip of water only if instructed. On smoking it is direct: quitting even one day before a procedure helps heart and lung function, and stopping two weeks ahead is better. For anyone flying in, that means the preparation window starts weeks before the flight, not on arrival.
Anesthesia: What Gets Decided, and by Whom
Anesthesia is a decision made with you, not handed to you. Cleveland Clinic describes four categories: local anesthesia, which numbs a small area while you stay awake; sedation, sometimes called twilight sleep, which relaxes you to the point of napping while remaining rousable; regional anesthesia, which blocks pain across a larger area; and general anesthesia, which makes you temporarily unconscious and is used for more invasive procedures including chest surgery.
Cleveland Clinic notes that for simple procedures the operating clinician often gives the local anesthetic, while for more complex procedures a physician anesthesiologist prescribes the medication and manages your pain before, during, and after surgery. It lists factors that raise anesthesia risk, among them advanced age, diabetes or kidney disease, a family history of malignant hyperthermia, heart or lung disease, obesity, sleep apnea, and smoking.
ASPS lists anesthesia risks first among the risks of gynecomastia surgery, and states that anesthesia is discussed at consultation. YONSEI LEEDS CLINIC does not publish an anesthesia protocol for this procedure; its own materials record anesthesia and pain control as a field still to be confirmed. Ask in writing what type is planned, who administers it, and who monitors you.
Step Five: The Day Itself
The clinic publishes an eight-step pathway: initial consultation and assessment, evaluation of glandular and fatty chest tissue, individualized planning, selection of the surgical approach based on tissue composition, the surgery performed by Dr. Khang, post-operative monitoring, compression-garment and activity guidance, then follow-up and remote support for international patients.
One practical thing before the operation is easy to overlook. ASPS states you will be asked to sign consent forms confirming that you understand the procedure and its risks and potential complications, and that those risks are fully discussed beforehand. If you need an interpreter or a written translation to make that consent meaningful, arrange it in advance rather than at the door; the clinic states that English-speaking consultations and translated documents are available.
The clinic states that the exact operative plan and expected duration should be confirmed with Dr. Khang at consultation, because the approach varies with whether the enlargement is primarily glandular, primarily fatty, or mixed. It does not publish a standard operating time, and no honest article can give you one.
Step Six: Dressings, Drains, and the Compression Garment
Recovery begins in the room where you wake up. ASPS states that dressings or bandages are applied to the incisions, that an elastic bandage or support garment may be used to reduce swelling and support the new chest contour while it heals, and that a small, thin tube may be temporarily placed under the skin to drain excess blood or fluid.
ASPS also describes what you go home with: instructions covering care of the surgical site and any drains, medications to aid healing and reduce infection risk, specific things to watch for, and when to return. Its suggested questions are worth asking out loud before discharge — what medication will I be given, when do the dressings come off, are stitches removed and when, when can I resume activity and exercise, and when do I come back.
The clinic states that its post-operative care includes follow-up assessments, compression-garment guidance, activity restrictions, return-to-exercise guidance, and scar-management advice, and that garment fit, wear schedule, and weaning are guided individually rather than issued as a fixed rule.
Step Seven: The Recovery Arc
The clinic publishes a staged chest-recovery program rather than a single discharge sheet. Days one to three cover post-operative assessment, wound and garment evaluation, and baseline documentation. Weeks one to two add swelling and lymphatic support alongside compression, activity, and wound-care instruction. Scar management may begin in weeks two to four, once the incision has closed adequately. Radiofrequency-based skin firmness care may be introduced in weeks four to eight where clinically appropriate. A mid-recovery evaluation falls around weeks six to eight, and a final review of scar maturation, firmness, and contour symmetry at months three to six.
The clinic states that visible swelling generally decreases substantially over roughly the first four to eight weeks, that scar visibility may keep improving over three to six months, and that firmness improvements may become more apparent from around week six. It also states that protocols are adjusted to each patient's observed healing rather than run to a fixed calendar.
The clinic is explicit in its own documentation that it should not claim guaranteed results, guaranteed symmetry, specific success rates, complication-free outcomes, or exact recovery timelines. Treat any published timeline, including this one, as a typical course rather than a promise about yours.
Scars, Swelling, and When the Result Is Actually the Result
ASPS states that gynecomastia surgery results are immediately visible, that swelling resolves and incision lines fade over time, and that the final result may take three to six months. It is equally direct about the trade-off: any surgical correction requires incisions, and all gynecomastia surgery scars are permanent, even where they are concealed within the natural contours of the chest.
ASPS also states plainly that surgery is not an exact science, that good results are expected but not guaranteed, and that optimal results may not always be achievable with a single procedure. Another operation may be needed for additional tightening or repositioning, or to treat a complication.
The clinic describes its own goal as a chest contour that is flat, natural, symmetrical, and durable, while noting that swelling and healing affect the early appearance and that patients should judge the result progressively rather than expecting the final contour immediately.
The Complication Set You Should Be Told About
ASPS publishes the risks of gynecomastia surgery for patients, and that list is what your consent conversation should cover: anesthesia risks, bleeding or hematoma, blood clots, breast asymmetry, contour and shape irregularities, changes in nipple or breast sensation, damage to deeper structures such as nerves, blood vessels, muscles and lungs, deep vein thrombosis and cardiac and pulmonary complications, fat necrosis, fluid accumulation or seroma, infection, persistent pain, poor wound healing, the possibility of revision surgery, reactions to tape or sutures, and unfavorable scarring.
ASPS gives one instruction for the period after you go home that is worth memorizing rather than filing: if you experience shortness of breath, chest pain, or an unusual heartbeat, seek medical attention immediately, because these may require hospitalization and further treatment. It adds that incisions should not be subjected to excessive force, swelling, abrasion, or motion during healing.
ASPS also notes that final results are permanent in many cases, but that where gynecomastia resulted from prescription medications, other drugs including steroids, or weight gain, maintaining the result depends on staying free of those substances and at a stable weight.
What YONSEI LEEDS CLINIC States About Its Pathway
YONSEI LEEDS CLINIC is a plastic surgery and aesthetic medicine clinic on the fifth floor of Il-i Tower in Seocho-gu, Seoul, roughly a minute from Gyodae Station Exit 12. It is led by Dr. In-Ho Khang, who holds an MD from Yonsei University College of Medicine and serves as Chief Academic Director of Plastic Surgery at the Korean Society of Aesthetic Surgery & Laser. The clinic identifies gynecomastia correction as one of its highest-volume specialties and lists it first among the procedures US patients request. His background appears on the clinic's doctor profile page.
The clinic describes Dr. Khang as a board-certified specialist without naming the issuing board, so the honest step for a US reader is to ask to see the certificate at consultation rather than treat the description as independently verified. The clinic also holds Korean registration as a Medical Institution for Attracting Foreign Patients, issued by the Ministry of Health and Welfare. That is a registration permitting the treatment of foreign patients; it is not a clinical quality accreditation and it is not a US-recognized credential.
On this procedure specifically, the clinic states that Dr. Khang personally conducts the consultation, the surgery, and the post-operative assessment, and that international patients receive pre-arrival teleconsultation, written pre-operative documentation, guidance on recommended length of stay, and remote follow-up after returning home. Inquiries and online consultations run through the clinic's contact page, and its full service list sits on the main clinic site.
What the clinic does not publish
Naming the gaps is more useful than guessing at them. The clinic does not publish an anesthesia and pain-control protocol for gynecomastia, a procedure-specific list of risks and contraindications, a standard operative time, case volumes or years in practice, booking lead times, a defined minimum stay in Korea, travel or accommodation logistics, revision policy specifics, or payment arrangements. Every one of those is a reasonable question to put in an email before you book a flight.
Flying Home, and the Clot Question
Seoul runs roughly 13 to 17 hours ahead of the continental United States, so a pre-arrival teleconsultation and any remote follow-up will usually mean an early-morning or late-evening call at your end.
The clinically important travel issue is venous thromboembolism, meaning deep vein thrombosis or pulmonary embolism. The CDC's Yellow Book lists recent surgery among the established risk factors for VTE, alongside limited mobility, obesity, age over 40, previous VTE, and inherited or acquired thrombophilia. It states that long-distance air travel may raise overall VTE risk roughly two- to four-fold, though the data are inconsistent, and that the magnitude correlates with both duration of travel and pre-existing risk factors. It notes that most travel-associated VTE occurs within one to two weeks after a flight and that risk returns to baseline by about eight weeks.
The CDC also summarizes society prevention guidance. The American College of Chest Physicians recommends, for higher-risk travelers on journeys over six hours, frequent walking, calf muscle exercises, an aisle seat, and properly fitted below-the-knee graduated compression stockings — a weak recommendation based on low-quality evidence. The American Society of Hematology suggests compression stockings or prophylactic low molecular weight heparin for travelers at substantially increased risk on journeys over four hours, and names recent surgery in that category.
None of that is a departure date. The clinic states it gives individual guidance on length of stay and on the timing of the first post-operative assessment; when you actually fly is a decision for the surgeon who operated on you.
The Bottom Line
- Gynecomastia correction is a sequence — cause workup, tissue assessment, technique decision, preparation, surgery, compression and wound care, then staged follow-up.
- Enlarged male breast tissue can have medical causes ranging from medications to liver, kidney, thyroid, and hormonal conditions, so a workup belongs before a cosmetic plan; one-sided enlargement or a firm lump should be evaluated medically first.
- The operative decision turns on whether the chest is glandular, fatty, or mixed, because liposuction removes fat while gland tissue generally requires excision.
- ASPS states final results may take three to six months and that all gynecomastia scars are permanent; the clinic states swelling generally settles substantially over about four to eight weeks.
- The clinic does not publish an anesthesia protocol, operative times, a minimum stay, or a revision policy, and describes Dr. Khang as board-certified without naming the issuing board — all worth resolving in writing before you travel.
Frequently Asked Questions
What is gynecomastia correction, in one sentence?
It is surgical treatment of enlarged male breast tissue, planned around whether that tissue is glandular, fatty, or both. Mayo Clinic describes the two options as liposuction, which removes breast fat but not gland tissue, and mastectomy, which removes the gland tissue and can sometimes be done through small incisions. The two are sometimes combined.
Do I need medical tests before gynecomastia surgery?
Usually some. Mayo Clinic states that blood tests, mammograms, CT or MRI scans, testicular ultrasound, and tissue biopsy may be ordered to find a cause or exclude conditions that look similar. Separately, ASPS states you may be asked to get lab testing or a medical evaluation as part of preparing for surgery.
Is gynecomastia surgery painful?
The clinic's published material states that some discomfort, soreness, swelling, or tightness can be expected afterward, that the amount varies between patients, and that pain management should follow the surgeon's instructions. ASPS states you will be given medications to take or apply. The clinic does not publish a pain-control protocol, so ask for it specifically.
Will I have a drain and a compression garment?
Possibly both. ASPS states that a small, thin tube may be temporarily placed under the skin to drain excess blood or fluid, and that an elastic bandage or support garment may be used to reduce swelling and support the healing contour. The clinic states that garment fit, wear schedule, and weaning are guided individually and reviewed at follow-up.
How visible will the scars be?
ASPS states that any surgical correction of gynecomastia requires incisions, that most incision lines are concealed within natural contours, that some may be visible, and that all such scars are permanent even when well placed. It adds that incision lines continue to fade over time. The clinic states scar management may begin once the incision has closed adequately.
When can I fly back to the United States?
That is a decision for the surgeon who operated on you, not a fixed number. The CDC lists recent surgery among the risk factors for travel-associated blood clots and notes that most such events occur within one to two weeks of a flight. The clinic states it provides individual guidance on length of stay and on the timing of the first post-operative assessment, but does not publish a minimum-stay policy.
Can gynecomastia come back after surgery?
ASPS states that final results are permanent in many cases, with one condition. Where the gynecomastia resulted from prescription medications, other drugs including steroids, or weight gain, keeping the result depends on staying free of those substances and at a stable weight. It advises discussing this with your physician before changing any prescription.
This article is for general informational purposes and does not constitute individualized medical advice, and it is not a self-diagnosis tool. Surgical candidacy, technique, and expected outcomes can only be determined through a consultation with a qualified plastic surgeon.
More Articles
Continue reading our clinical guides.
Why Korea Body Contouring Prices Stay Low Despite Global Inflation Rise
While global inflation has driven up the cost of surgical procedures in many Western markets, Korean body contouring clinics have maintained stable pricing through efficiency and modern liposuction protocols.
Learn More

Breast Fat Grafting Costs: Korea vs Japan Price Comparison 2026
Autologous breast fat grafting uses a patient's own fat cells to enhance breast volume and shape. Compare 2026 breast fat grafting costs and SVF systems in South Korea vs Japan.
Learn More

Body Lift Efficacy: 90% Satisfaction in Korean Reconstruction Studies
The human body undergoes profound structural modifications following significant weight loss, childbirth, or natural structural aging. Learn how high-precision body lift surgery in Korea achieves 90% patient satisfaction.
Learn More