Personalized Plastic Surgery & Aesthetic Care in Seocho-gu, Seoul

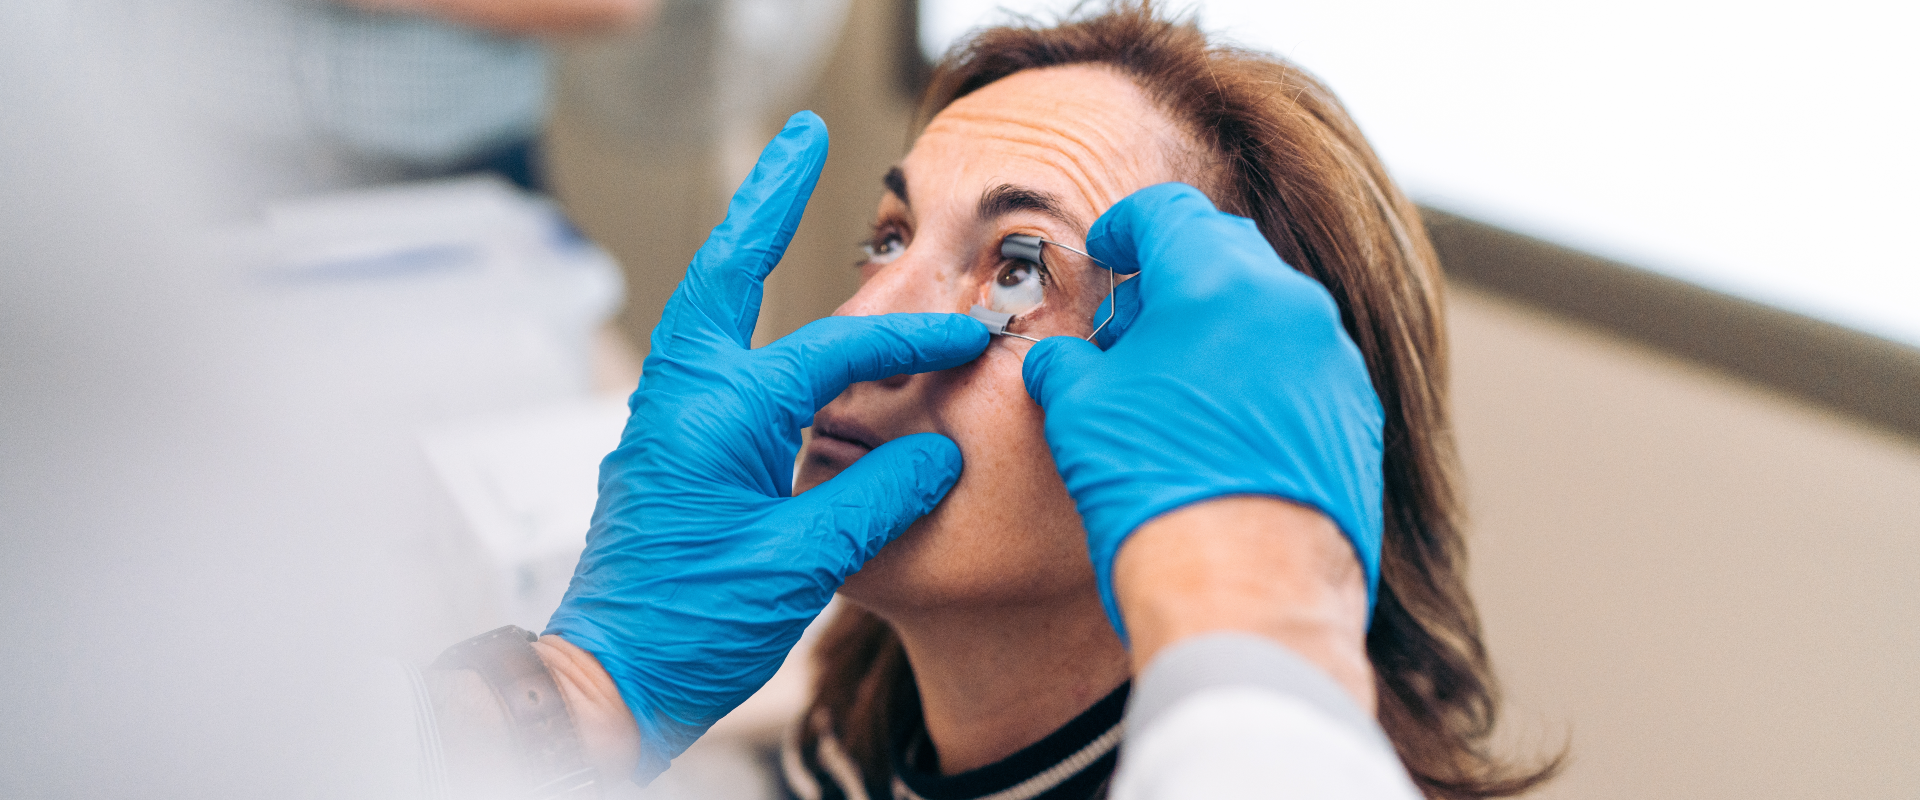
Medical Guide
Double Eyelid Surgery, Ptosis Correction, Epicanthoplasty
Double eyelid surgery, ptosis correction and epicanthoplasty solve different anatomical problems. Here is how Korean eyelid surgeons choose between them.
Schedule a ConsultationEyelid Surgery Explained: Which Operation Solves Which Anatomical Problem
Medically reviewed by Dr. In-Ho Khang, MD, Yonsei University College of Medicine; Chief Academic Director of Plastic Surgery, Korean Society of Aesthetic Surgery & Laser (KSASL)
Most people researching double eyelid surgery in Korea pick a procedure name first and look for a surgeon second. That order is backward. Double eyelid surgery, ptosis correction and epicanthoplasty operate on three different structures, and the finding on your eyelid decides which one applies. This article takes each operation in turn and maps the findings surgeons measure onto the five eye procedures YONSEI LEEDS CLINIC in Seoul describes.
Four Findings, and the Operations That Match Them
Separate the findings from the procedure names. Four things can be wrong around the eye, in any combination.
The crease. The upper lid may have no crease, or one that sits low, shallow or uneven. That is a question about where skin attaches to the tissue beneath it, and crease creation surgery addresses it.
Lid height. The upper lid margin may rest lower over the eye than it should. That is ptosis, a problem of the muscle and tendon that lift the lid, and crease work does not correct it.
The inner corner. A fold of skin may cover part of the medial canthus, the innermost point where the lids meet. Adjusting that fold is epicanthoplasty.
Tissue volume. Excess skin, displaced fat and laxity are the territory of upper and lower blepharoplasty, two different operations on two different compartments.
A narrower fifth question, the horizontal width of the eye opening, is what lateral canthoplasty addresses. YONSEI LEEDS CLINIC names five: double eyelid creation, ptosis correction, epicanthoplasty, lateral canthoplasty and lower blepharoplasty, each addressing a different anatomical concern.
Double Eyelid Surgery: Building an Attachment, Not Drawing a Line
A crease is not a line on the skin. A StatPearls review of upper eyelid blepharoplasty on the NIH's NCBI Bookshelf describes the eyelid crease as the place where the levator aponeurosis, the flat tendon sheet transmitting the pull of the lid-lifting muscle, attaches to the dermis. Crease surgery builds a durable attachment between skin and a deeper structure, and everything else in the operation serves that attachment.
Vocabulary is a real obstacle. A review in Archives of Aesthetic Plastic Surgery, the journal of the Korean Society for Aesthetic Plastic Surgery, proposes "supratarsal crease surgery" as the neutral term and notes that what is marketed as the non-incisional or suture method is more precisely a microincisional buried suture technique — meaning small openings rather than none, and no continuous incision along the crease line.
The Buried Suture Route: What You Trade
The review sets out the trade in specifics.
In its favor: minimal external scarring and shorter recovery, with the thin-lid patient described as the ideal candidate. Against it: reduced visualization of tissue, greater difficulty producing a parallel crease because the fold can vanish toward the nose, and permanent buried sutures left in the lid. Complications listed: suture failure with loss of the crease, suture erosion, palpable sutures, asymmetry, partial crease formation, and a feeling of strain.
A four-year retrospective cohort in the same journal followed 1,500 buried-suture double eyelid cases and reported an overall reoperation rate of 19.7 percent, with rates differing significantly between suture configurations and a continuous method lowest. This is a durability trade rather than a free upgrade, and the specific design matters.
Incisional and Partial-Incision Crease Surgery
The incisional approach uses a continuous opening along the planned crease. The review describes its ideal candidate broadly: all patients, and especially revision cases, thick lids, and lids with dermatochalasis. Its advantages are direct visualization, the ability to correct ptosis in the same operation, selective debulking of tissue, better control of bleeding, and precise repositioning of the fat in front of the levator. Its disadvantages are longer recovery and a steeper learning curve.
Its characteristic complications are asymmetry and what the review calls static crease deformity, in two forms: a depressed scar after removal of too much orbicularis muscle, and an excessively deep fold after anchoring the lower skin edge too high. Both are design problems, which is why crease height and depth are planning decisions. A partial-incision approach sits between the two, using limited openings so that some tissue can be addressed directly.
YONSEI LEEDS CLINIC states that the chosen route may be incisional, partial incision or non-incisional according to anatomy, and that crease height, shape and depth are designed individually, in parallel, tapered or semi-tapered form. It states that incisional surgery is long-lasting under normal aging and that the suture method can also produce a durable crease in appropriate candidates, while individual eyelid characteristics influence how long a crease lasts. It describes no eyelid result as permanent.
Ptosis Correction: A Muscle and Tendon Problem
The StatPearls review of blepharoptosis defines ptosis as abnormal drooping of the upper eyelid in primary gaze, and makes a point that reframes everything: ptosis is a clinical sign, not a diagnosis. It may be congenital or acquired, and isolated or part of a systemic condition.
The lid is lifted mainly by the levator palpebrae superioris, supplied by the third cranial nerve, with a smaller contribution from the Müller muscle. Disruption anywhere along that pathway produces ptosis, and the review classifies true ptosis as aponeurotic, neurogenic, myogenic, mechanical or traumatic. Aponeurotic ptosis is the most common adult form, usually appearing in the fifth or sixth decade, and follows the aponeurosis separating from or thinning at its attachment.
Some presentations are not cosmetic at all. The review notes that sudden ptosis with headache or pupil changes raises concern for compressive third nerve palsy and calls for urgent imaging, and that ptosis fluctuating through the day suggests ocular myasthenia gravis. A drooping lid deserves a diagnosis before it is offered an operation.
Ptosis, Dermatochalasis and Brow Ptosis Are Three Different Findings
These findings look alike in a mirror but call for different operations.
The blepharoptosis review separates true ptosis, caused by dysfunction of the lifting mechanism itself, from pseudoptosis, in which the lid only looks low. It names dermatochalasis, brow ptosis, hypotropia and abnormal globe position as extrinsic causes.
Dermatochalasis is the excess-skin finding. The upper eyelid blepharoplasty review defines it as laxity or redundancy of eyelid skin and muscle, attributed to loss of elastic tissue, thinning of the epidermis, weakened connective tissue and aging, with a strong genetic component. It uses a separate term, steatoblepharon, for prominence of the eyelid fat pads, and notes both are usually noticed in the fourth decade. Blepharoplasty removes or repositions skin and fat; it does not change lid height.
Brow ptosis is descent of the eyebrow itself. The StatPearls chapter on it states the condition is almost always acquired, that the age-related form is the most common, and that laxity of connective tissue, skin and the frontalis muscle first drops the lateral third of the brow. Patients describe this as drooping eyelids. The chapter gives the maneuver that separates the two: elevate the brow manually to neutral, and if the lid is still low, the finding is true blepharoptosis rather than pseudoptosis.
Three findings, three answers: levator surgery for a low lid margin, skin and fat surgery for redundancy, brow surgery for a descended brow.
How Ptosis Is Measured
Marginal reflex distance 1, or MRD1, is the distance from the corneal light reflex to the upper lid margin, and the review gives 4 to 5 millimeters as normal. In one-sided ptosis, a 2 millimeter difference between the eyes is graded mild, 3 millimeters moderate and 4 millimeters severe.
Levator function is described as the most critical measurement because it determines the approach directly. It is lid excursion from maximal downgaze to maximal upgaze with the brow held still. Normal excursion exceeds 15 millimeters, and the review grades function in four steps, from poor at the low end to excellent above 12 millimeters. Because that measurement drives the choice of operation, ask for your number in millimeters rather than the grade label. Poor function typically calls for a frontalis sling, which harnesses brow movement, rather than a levator-based repair.
Levator aponeurosis advancement is described as the procedure of choice for aponeurotic ptosis, and can be combined with upper blepharoplasty where dermatochalasis coexists. A Müller muscle and conjunctival resection, performed from inside the lid, has narrower criteria: mild to moderate ptosis, levator function of at least 10 millimeters, and a positive phenylephrine test.
In one-sided ptosis, a Hering test lifts the drooping lid to see whether the other one falls, and the review states patients should be counseled about possible surgery on the second lid.
When This Belongs to an Ophthalmologist
Some of what looks cosmetic is functional. An American Academy of Ophthalmology technology assessment concluded that repair of blepharoptosis and of upper eyelid dermatochalasis provides significant improvement in vision, peripheral vision and quality-of-life activities. Among the preoperative indicators it listed: MRD1 of 2 millimeters or less, superior visual field loss of at least 12 degrees or 24 percent, downgaze ptosis interfering with reading, and a chin-up backward head tilt.
The Academy's patient guidance states that ptosis can limit peripheral or central vision, that correction works by shortening and strengthening the lid muscle, and that before surgery the ophthalmologist does a complete eye examination and may also photograph the eyes and test side vision. Mayo Clinic lists tear production testing, visual field testing and photography among standard preoperative steps.
If your lids affect what you can see, that is a functional matter and an eye examination should come before a cosmetic plan. Eyelid surgery in the United States is performed by ophthalmologists, oculoplastic surgeons and plastic surgeons; the American Society of Ophthalmic Plastic and Reconstructive Surgery describes its members as board-certified physicians with ophthalmology residency plus fellowship training in eyelid and orbital surgery. The clinic states its consultation includes assessment of the degree of ptosis; it does not publish whether visual field testing is performed.
Epicanthoplasty: Adjusting the Inner Corner
Epicanthoplasty modifies the epicanthal fold, the skin fold covering part of the inner corner. It lengthens the eye toward the nose, has no effect on lid height, and affects the crease only indirectly.
That indirect effect is why it is discussed alongside crease surgery. The Archives of Aesthetic Plastic Surgery review explains that a small or absent fold is favorable for a patient who wants a parallel crease, and notes the reverse: in patients with a very large caruncle, the small pink tissue at the innermost corner, it may be advisable not to perform epicanthoplasty at all. YONSEI LEEDS CLINIC states that it designs the epicanthoplasty around the double eyelid line it intends to create, not as a standalone step.
Design magnitude decides the outcome. The review describes a much shorter incision when the goal is only to release the tension the fold creates, and warns that extending the design too far produces overcorrection, with a stretched appearance and pronounced caruncular show.
The scar question deserves an honest answer. The incision sits on thin, exposed skin at the medial canthus, where no crease conceals it. The review states that most epicanthoplasty scars mature to an imperceptible state over at least three months, and that carbon dioxide laser resurfacing or steroid micro-injection can be used where a scar stays thickened. This is the eyelid operation where a recommendation against it is often correct.
The outer corner is a separate question. Lateral canthoplasty targets the horizontal dimension of the eye opening; the clinic names a more open and elongated eye shape among its described outcomes, attributes wider- or softer-looking eyes to epicanthoplasty instead, and states that this operation may be combined with double eyelid surgery or epicanthoplasty.
Upper Versus Lower Blepharoplasty: Two Different Compartments
Blepharoplasty covers two operations that share little beyond a name.
Upper Blepharoplasty
Upper eyelid blepharoplasty is a tissue-volume operation. Mayo Clinic describes cutting along the fold of the lid, removing some excess skin, muscle and possibly fat, and closing the incision. The American Society of Plastic Surgeons lists what it treats: loose skin that disturbs the natural contour and sometimes impairs vision, and fatty deposits that appear as puffiness.
What it does not do is raise the lid margin. Mayo Clinic makes the interaction explicit: if the upper lid droops close to the pupil, blepharoplasty may be combined with a ptosis procedure to lift the lid as well as remove excess skin. Brow position belongs in the same assessment.
Lower Blepharoplasty
The lower lid is a different structure with a different failure mode. A StatPearls chapter on transconjunctival lower lid blepharoplasty describes three post-septal fat compartments and the tear trough at the transition from lid to cheek, and sets out two approaches: transconjunctival, from inside the lid, and transcutaneous, through an incision below the lashes.
Selection follows the findings. The chapter describes the transconjunctival approach as best suited to prominent fat with minimal to moderate lid laxity and good skin elasticity, and notes that repositioning fat rather than removing it can address a tear trough. Where skin excess is meaningful, a conservative skin pinch is a secondary maneuver.
Laxity testing protects the result. The chapter describes the snap test, in which the lid is pulled down and should return immediately, and the distraction test, in which pulling the lid more than 6 millimeters from the eye is abnormal. Patients with lower lid laxity are prone to lid malposition after surgery, and suture canthopexy is described as support where laxity is minimal. The complication list is compartment-specific: lid retraction, ectropion, lagophthalmos, strabismus from injury to the inferior oblique muscle, corneal abrasion, and rarely orbital hemorrhage, which can threaten sight. Unrecognized dry eye or orbital disease is named as a reason to refer to an ophthalmologist first.
YONSEI LEEDS CLINIC states that its lower blepharoplasty aims to preserve a natural contour during under-eye fat removal, takes approximately 30 to 40 minutes under sedation anesthesia, requires no hospitalization, and typically allows a return to daily activities the following day. Its published risk statement is briefer: temporary swelling, bruising and sensitivity, with healing rates varying. The American Society of Plastic Surgeons list is the fuller one to walk through at consent, covering dry eyes, difficulty closing the eyes, ectropion, lid lag, unfavorable scarring, possible revision surgery, temporary or even permanent change in vision, and a very rare chance of blindness.
How These Operations Are Combined
Combination is the norm, for anatomical reasons. The clinic states that double eyelid surgery may be paired with ptosis correction where both crease and lid position need work.
Technique choice interacts with that. The Archives of Aesthetic Plastic Surgery review lists simultaneous ptosis correction among the advantages of the incisional crease technique, so the crease technique chosen can constrain what else is possible in the same operation. Lower lid surgery pairs with canthopexy for support rather than appearance. More procedures in one sitting means more swelling and a longer wait before the result can be judged, so ask what could be staged.
What the Consultation Should Establish
YONSEI LEEDS CLINIC describes a consultation with Dr. In-Ho Khang covering concerns, goals and medical history, followed by an assessment of eyelid anatomy it lists in detail: degree of ptosis, inner-corner fold characteristics, skin thickness and redundancy, fat distribution in both lids, and how the eyes sit within overall facial proportions. The plan — route, crease height and shape, corner design, any added procedure — is settled before the operation.
No second physician is listed. The clinic states that Dr. Khang holds an MD from Yonsei University College of Medicine, serves as Chief Academic Director of Plastic Surgery at the Korean Society of Aesthetic Surgery and Laser, and counts upper and lower blepharoplasty and eye reshaping among his specialties; his doctor profile page is the published record. It describes him as a board-certified specialist without naming the issuing board, so treat that as its own statement and ask to see the certificate, since Korea has no public individual specialist registry.
Six questions are worth writing down.
- What is my MRD1 in each eye, and do I have ptosis?
- What is my levator function, and does it allow a levator-based repair?
- If I have excess skin, is my brow position contributing to it?
- Which crease technique are you recommending, and what about my lid leads you there?
- Do I need epicanthoplasty at all, or is a shorter tension-releasing design enough?
- For lower lid work, what did the laxity tests show, and is canthal support planned?
Several answers are not published and should be requested in writing: contraindications, expected pain, the anesthesia used for upper-lid procedures, minimum length of stay, and any revision policy. The clinic's own materials mark these as needing confirmation.
Recovery Differs by Operation
The clinic states that swelling resolves progressively over the weeks after surgery, and that the finished result — matured scars and a settled crease — arrives over roughly three to six months, varying with the operation and individual healing.
Mayo Clinic states that bruising and swelling generally lessen over about 10 to 14 days, that scars may take months to fade, and that severe new eye pain, bleeding or vision problems warrant immediate attention.
The clinic publishes no fixed minimum stay, only that patients should allow time for surgery, early follow-up and an assessment before the flight home. It states that online consultation, English-language support and remote follow-up are available. Seoul runs roughly 13 to 17 hours ahead of the continental United States, so schedule remote calls with that offset in mind; its inquiry and consultation page is the published route.
The Bottom Line
- Crease creation, ptosis correction, epicanthoplasty and blepharoplasty address four independent findings: skin-to-tendon attachment, lid margin height, the medial canthal fold, and tissue volume.
- Ptosis, dermatochalasis and brow ptosis all look like a drooping eyelid and call for three different operations; lifting the brow by hand to see whether the lid is still low is a documented way to separate the last two from true ptosis.
- The suture-versus-incision choice is a trade rather than an upgrade: buried sutures mean less external scarring and faster recovery, an incision allows tissue debulking and simultaneous ptosis correction.
- Epicanthoplasty sits on thin, exposed skin, most of its scars mature over at least three months, some need active treatment, and overcorrection produces a stretched inner corner that is hard to reverse.
Frequently Asked Questions
Do I need double eyelid surgery or ptosis correction?
They answer different questions, and you can need both. Crease surgery decides where the fold sits; ptosis correction decides how high the lid margin sits. The distinction is made by measuring the distance from the corneal light reflex to the lid margin and by testing how far the lifting muscle moves the lid, neither of which is possible from a photograph.
What is the real difference between non-incisional and incisional double eyelid surgery?
The buried suture method creates the crease through small openings and leaves permanent sutures in the lid, offering minimal external scarring and shorter recovery. The incisional method uses a continuous opening, allowing direct visualization, selective tissue removal, fat repositioning and simultaneous ptosis correction, at the cost of longer recovery. Published guidance describes thin lids as favorable for the suture route, and thick lids, revision cases and excess skin as favorable for an incision.
Will a suture-method crease last?
Often, but the design matters. A four-year study of 1,500 buried-suture double eyelid cases reported an overall reoperation rate of about 20 percent, with significant differences between suture configurations. Loss of the crease, suture erosion and palpable sutures are recognized complications, so ask which configuration is planned.
How do I know whether my problem is excess skin or a drooping brow?
An examiner can lift your brow to a neutral position and look again. If the lid margin is still low with the brow supported, the finding is true ptosis of the lid; if the appearance improves, redundant skin and brow descent are doing the work. That single maneuver decides whether the operation should be on the lid, on the skin, or on the brow.
Is epicanthoplasty scarring visible?
In the early months, usually to some degree, because the incision lies on thin skin at the inner corner where no crease conceals it. Published guidance describes most scars maturing to an imperceptible state over at least three months, with laser resurfacing or steroid injection available for scars that stay thickened. Ask your surgeon to show you the intended design and its length beforehand.
Could my eyelid problem be a vision problem rather than a cosmetic one?
It can be, and that changes who should look at it first. An American Academy of Ophthalmology assessment identifies indicators including a marginal reflex distance of 2 millimeters or less, superior visual field loss of at least 12 degrees, downgaze ptosis interfering with reading, and a chin-up head tilt. If any of those describe you, see an ophthalmologist or oculoplastic surgeon before booking cosmetic surgery abroad.
This article is for general informational purposes and does not constitute individualized medical advice, and it is not a self-diagnosis tool. Surgical candidacy, technique, and expected outcomes can only be determined through a consultation with a qualified plastic surgeon.
More Articles
Continue reading our clinical guides.
Why Korea Body Contouring Prices Stay Low Despite Global Inflation Rise
While global inflation has driven up the cost of surgical procedures in many Western markets, Korean body contouring clinics have maintained stable pricing through efficiency and modern liposuction protocols.
Learn More

Breast Fat Grafting Costs: Korea vs Japan Price Comparison 2026
Autologous breast fat grafting uses a patient's own fat cells to enhance breast volume and shape. Compare 2026 breast fat grafting costs and SVF systems in South Korea vs Japan.
Learn More

Body Lift Efficacy: 90% Satisfaction in Korean Reconstruction Studies
The human body undergoes profound structural modifications following significant weight loss, childbirth, or natural structural aging. Learn how high-precision body lift surgery in Korea achieves 90% patient satisfaction.
Learn More